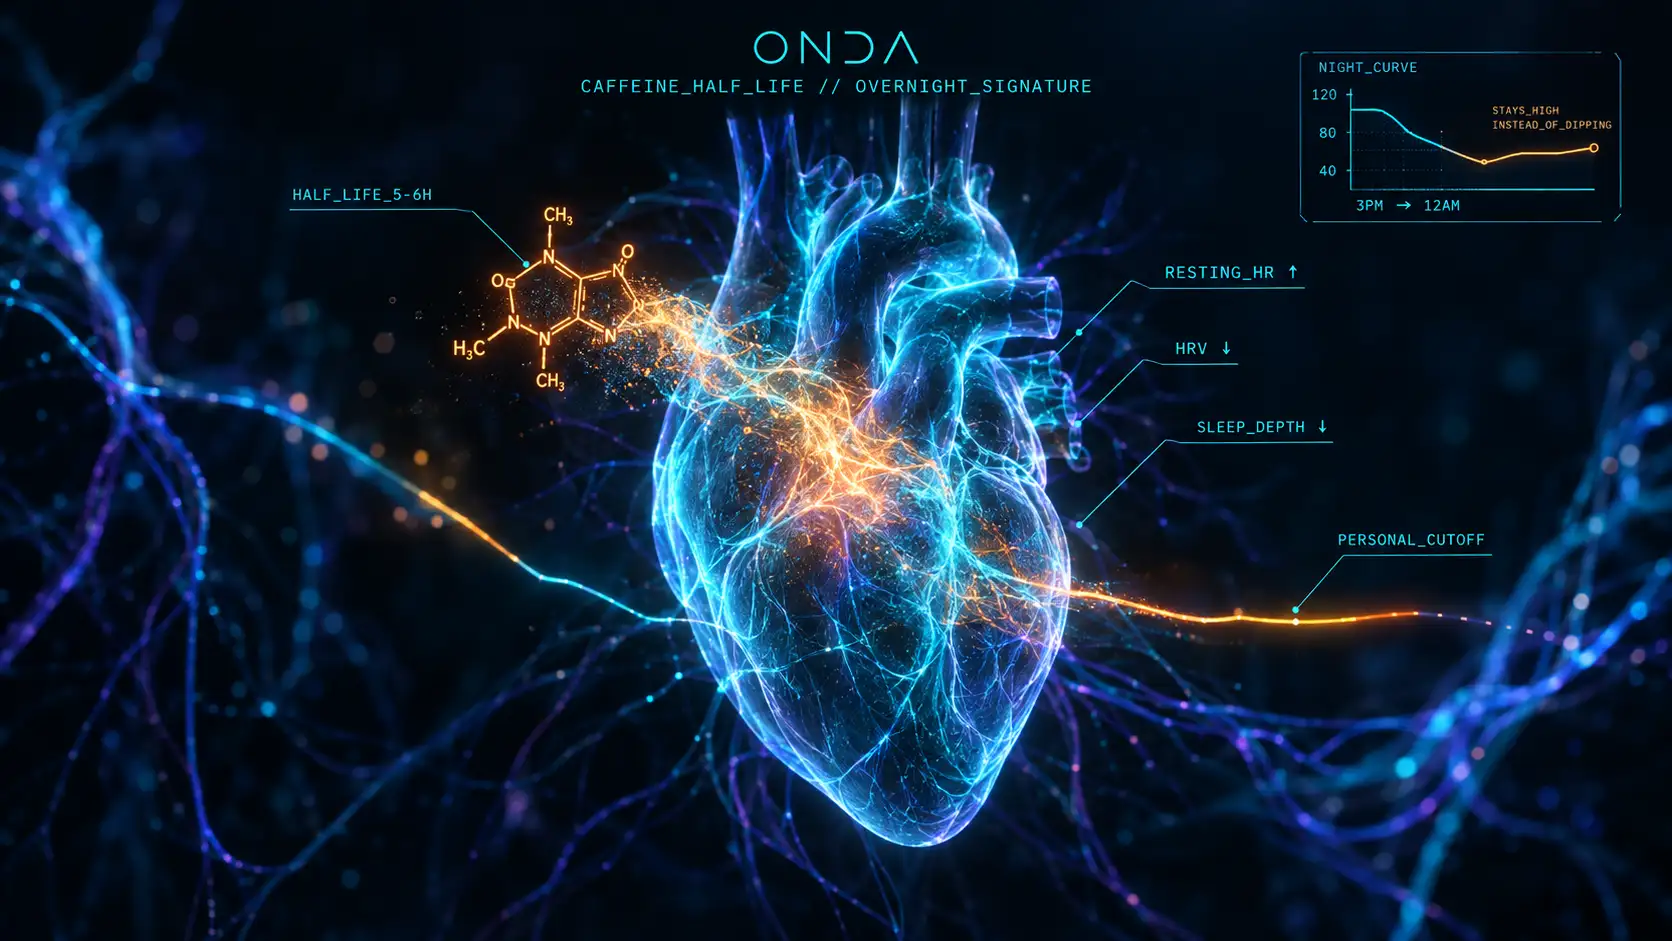
[ CASE FILE: THE CUP YOU FORGOT ABOUT ]
"You stopped tasting the coffee at three in the afternoon. Your heart is still tasting it at midnight.
Caffeine is the most-used stimulant on earth and the one people most confidently misjudge. The buzz fades in a couple of hours, so the story ends there — except the molecule doesn't. Half of that 2 p.m. cup is still circulating at dinner, quietly holding your nervous system a notch toward go while your body is trying to shift toward rest."
Section 1: How long does caffeine stay in your body?
Caffeine's half-life averages five to six hours. That is the number almost nobody accounts for. A coffee at 3 p.m. means roughly half its caffeine is still in you at 8 or 9 p.m., and a meaningful fraction past midnight. You don't feel it as a jolt anymore — tolerance blunts the sensation long before it clears the effect — but your autonomic nervous system is still reading it.
Caffeine is a stimulant, so the result is a body kept a little more alert into the night, exactly when it should be winding down into rest and recovery.
Section 2: Does caffeine affect your HRV and resting heart rate at night?
It can, though less predictably than the usual advice suggests. Here is what the evidence says about three things ONDA actually watches:
- •Resting heart rate may tick up — or may not. Caffeine can raise heart rate in some people, but its effect on resting heart rate is inconsistent across studies, and regular coffee drinkers develop tolerance. If it moves yours, it will show against your own corridor.
- •Overnight HRV may dip, mostly through sleep. The direct evidence is mixed: some studies find small changes in beat-to-beat variability after caffeine, others find none, and regular drinkers develop tolerance. The clearer link runs through sleep. Late caffeine can make sleep lighter and shorter, and a poorer night is one of the things that pulls overnight HRV down.
- •Sleep thins. Even when you fall asleep fine, caffeine can shave sleep quality and depth — and a poorer night drags the next day's baseline with it.
None of this is dramatic on any single night. It is a tax, not a catastrophe — and taxes compound.
Section 3: What time should you stop drinking coffee?
There's no universal cutoff — here is the part the "no caffeine after 2 p.m." rule gets wrong: the right cutoff is not the same for two people, and it isn't willpower. It's genetics and metabolism. Fast metabolizers clear caffeine quickly and can drink it late with little cost; slow metabolizers carry an afternoon cup deep into the night. Habitual heavy users develop partial tolerance to the acute autonomic effect; occasional users get hit harder.
So a population rule is the wrong tool. The only cutoff that means anything is yours, and the only way to find it is to watch how your own overnight numbers respond to caffeine at different times.
Section 4: Finding your cutoff from your own data
This is a measurement problem, and it's a solvable one. Build a personal baseline — your normal resting heart rate, variability and breathing rate — then watch what a late cup does to it. A night after a 4 p.m. coffee that reads with a higher resting pulse or a lower HRV than your corridor is your body drawing the line for you.
ONDA reads those signals in Apple Health (Apple Watch or another tracker that syncs there), or your resting numbers from the phone camera, and holds your corridor, so a late-caffeine night shows up as a visible departure from your normal rather than an abstract worry — your data, your line. Move the cup earlier, watch the night come back into the corridor, and you've found your cutoff empirically instead of guessing.
The honest caveat: caffeine affects sleep and recovery, but it isn't a medical hazard for most people and ONDA isn't diagnosing anything — it's showing you a lifestyle input written into your own numbers. For the adenosine-and-sleep-pressure side of the same molecule, see caffeine's half-life and sleep pressure.
Section 5: What to actually do
You don't have to quit coffee. You have to time it. Front-load caffeine into the morning, set your personal cutoff a few hours earlier than you think you need, and if you want the night back without giving up the ritual, a slow exhale-led wind-down helps hand the nervous system over to recovery. Then check the numbers — the corridor tells you whether it worked.
The Hack: Treat caffeine like a half-life, not a buzz. Assume a 3 p.m. cup is still working at 9 p.m., set your cutoff by what your overnight resting heart rate and HRV actually do — not by a generic rule — and move it earlier until your nights sit back inside your baseline.
HALF_LIFE: ~5-6h (afternoon cup active into the night) SIGNATURE: sleep depth ↓ · overnight HRV: debated (mostly via sleep) · resting HR: inconsistent (tolerance in regular drinkers) CUTOFF: personal (genetics/metabolism), not a fixed clock METHOD: read your own baseline — PRACTICE, NOT DIAGNOSIS[ SYSTEM_STATUS ]